
FPGEE Study Plan: A 16-Week Step-by-Step Preparation Guide
Preparing for the FPGEE can feel difficult for one simple reason:
There is a lot to cover.
You are not studying only pharmacology.
The current FPGEE Content Outline includes biomedical sciences, pharmaceutical calculations, medicinal chemistry, pharmacology, pharmaceutics, pharmacokinetics, pharmacogenomics, compounding, biostatistics, pharmacy management, health care systems, communication, ethics, evidence evaluation, and clinical pharmacy.
Trying to study all of that without a structure often creates the same cycle:
Read a chapter → forget part of it → move to another chapter → feel behind → restart old material → never reach cumulative practice.
A better approach is to divide preparation into phases.
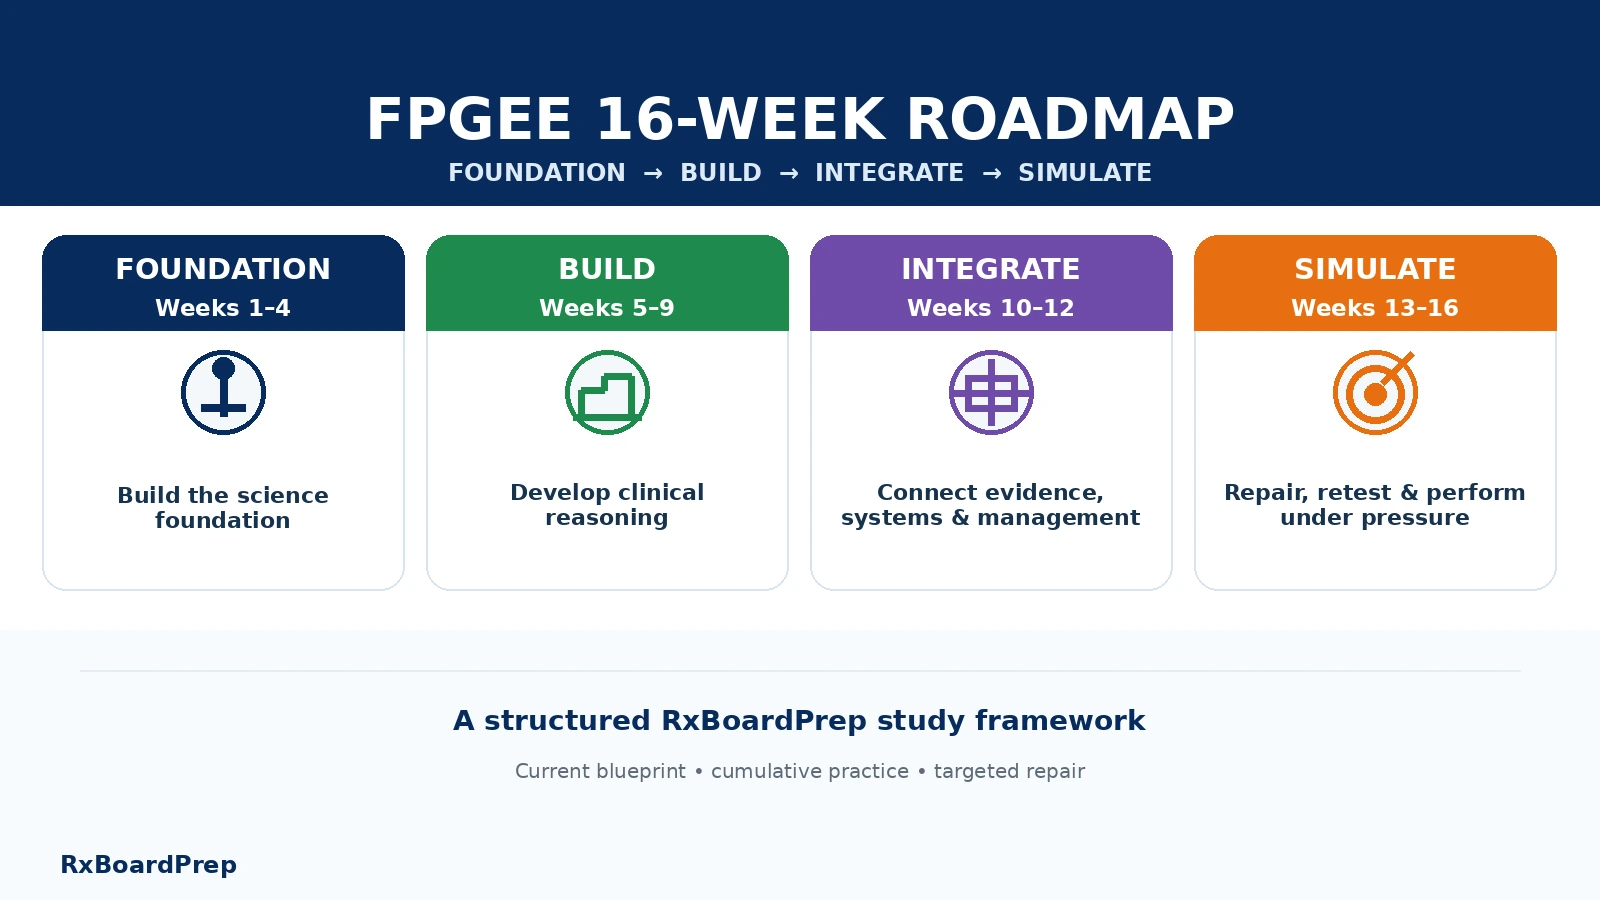
This 16-week FPGEE study plan is built around four goals:
FOUNDATION → BUILD → INTEGRATE → SIMULATE
You will first build the science foundation, then cover the major pharmaceutical and clinical subjects, integrate the administrative and evidence-based domains, and finally convert everything into exam performance through cumulative review and mock testing.
First: Understand What the FPGEE Actually Covers
The current NABP FPGEE Content Outline contains four major domains:
| Domain | Approximate Weight | Approximate Scored Questions |
|---|---|---|
| Foundational Biomedical Sciences | 12% | 24 |
| Pharmaceutical Sciences | 31% | 62 |
| Social, Behavioral, and Administrative Sciences | 20% | 40 |
| Pharmacy Practice and Clinical Sciences | 37% | 74 |
These approximate question counts are derived from the 200 scored-question framework and are included only to help visualize the relative weighting.
Two lessons immediately follow.
Lesson 1: Pharmaceutical + Clinical Sciences Dominate
Domains 2 and 4 together represent approximately 68% of scored questions.
That means your plan needs substantial time for:
- pharmacology
- medicinal chemistry
- pharmaceutics
- pharmacokinetics
- calculations
- compounding
- clinical disease states
- laboratory interpretation
- drug interactions
- monitoring
- patient-specific decision-making
Lesson 2: You Still Cannot Ignore the Other Domains
Biomedical Sciences and Social, Behavioral, and Administrative Sciences together represent approximately 32% of scored questions.
That represents a substantial portion of the examination.
Ignoring microbiology, immunology, biostatistics, management, health care systems, ethics, communication, or public health can create a major gap.
If you have not reviewed the current blueprint yet, start with our 2026 FPGEE Content Outline Explained before using this schedule.
The RxBoardPrep 16-Week Framework
The plan has four phases:
| Phase | Weeks | Goal |
|---|---|---|
| Phase 1 — FOUNDATION | 1–4 | Build biomedical + pharmaceutical fundamentals |
| Phase 2 — BUILD | 5–9 | Develop clinical reasoning across major disease states |
| Phase 3 — INTEGRATE | 10–12 | Master evidence, management, systems, ethics, communication |
| Phase 4 — SIMULATE | 13–16 | Cumulative repair, mixed questions, mock exams, final review |
The phases are not isolated.
Calculations, medicinal chemistry, drug interactions, statistics, and older material should continue appearing throughout the entire plan.
Before Week 1: Establish Your Baseline
Do not begin your 16-week plan by assuming you know where your weaknesses are.
Measure them.
Take a mixed baseline assessment containing questions from:
- biomedical sciences
- calculations
- pharmacology
- pharmacokinetics
- medicinal chemistry
- clinical pharmacy
- biostatistics
- management
- health care systems
Then classify your mistakes.
Use categories such as:
Knowledge
You did not know the information.
Application
You knew the concept but could not apply it.
Calculation
The setup, formula, units, or arithmetic failed.
Chemistry / Structure
You did not recognize the chemical principle, structure, metabolism, or SAR concept.
Data / Graph
You could not interpret the graph, PK curve, laboratory result, or statistical information.
Misread
You knew the concept but answered a different question.
This baseline is not there to tell you whether you will pass.
It tells you where your 16 weeks should spend extra time.
Your Weekly Study System
Before looking at the individual weeks, establish a repeatable weekly rhythm.
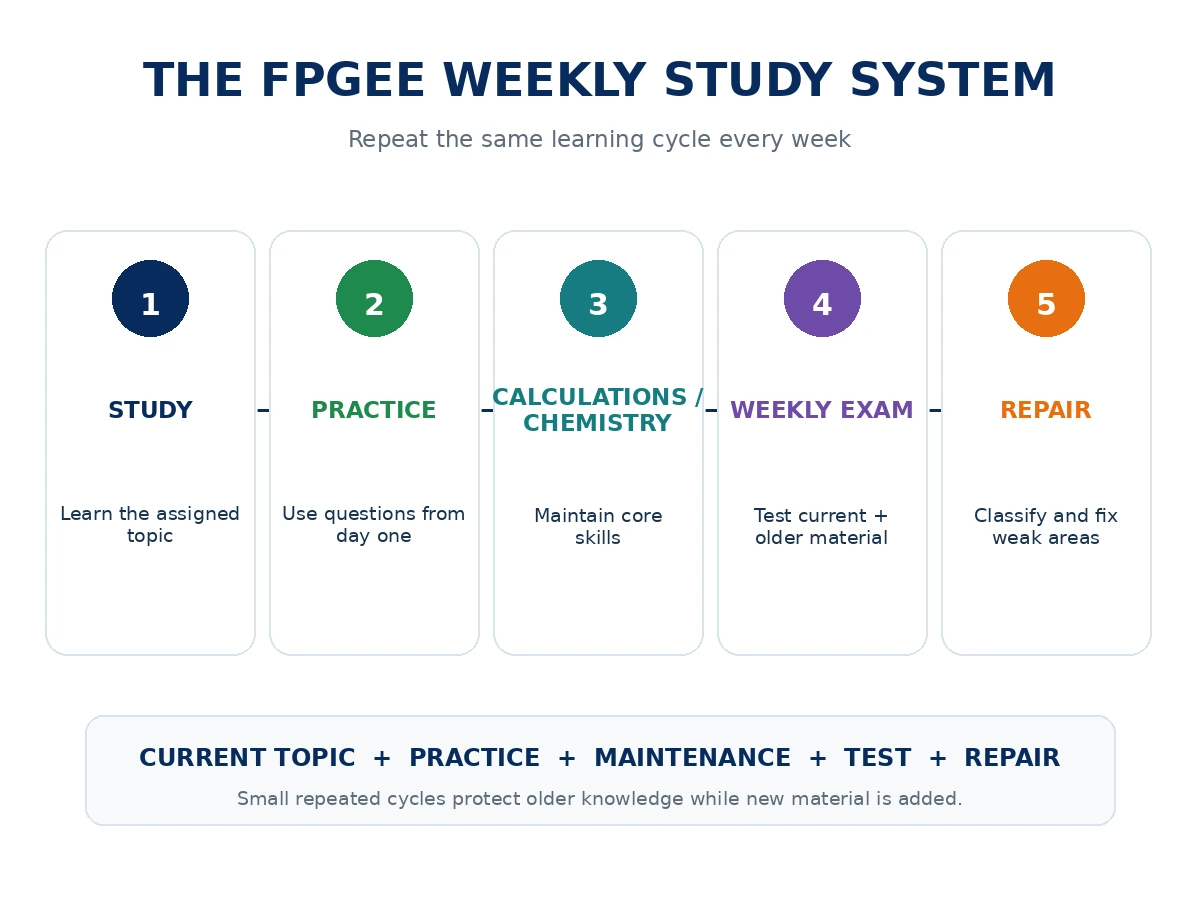
A strong week should include five things.
1. Main Content Study
Learn the assigned topic in an organized way.
Do not simply highlight pages.
Ask:
- What is the concept?
- Why does it matter?
- How could it become a question?
- What would make one answer choice better than another?
2. Daily Questions
Do not wait until Week 12 to begin solving questions.
Questions should start in Week 1.
They reveal whether you can actually use what you studied.
3. Small Daily Calculations Practice
Calculations deteriorate when they are studied once and abandoned.
Even during a clinical week, keep a small calculation rotation.
Examples:
- concentrations
- ratios
- molarity
- mEq
- infusion rates
- pharmacokinetics
- biostatistical calculations
4. Small Medicinal Chemistry Rotation
You do not need to memorize hundreds of structures every night.
But repeatedly revisit high-value concepts:
- functional groups
- acid/base behavior
- pKa and ionization
- stereochemistry
- metabolic transformations
- pharmacophores
- major SAR patterns
- selected important drug structures
This keeps medicinal chemistry from becoming an enormous last-minute memorization project.
5. Weekly Cumulative Exam
At the end of the week, test:
Current week + older material
Then review every important mistake.
A weekly exam should answer:
What needs to be repaired before I move deeper into the course?
A Practical Monday–Friday Routine
For a student studying around work or family responsibilities, a weekday session might look like:
Main Study
60–90 minutes
Practice Questions
30–45 minutes
Calculations or Chemistry
20–30 minutes
Error-Log Review
10–15 minutes
You can lengthen or shorten this depending on your schedule.
The structure matters more than the exact clock time.
The Catch-Up Rule
This may be one of the most important rules in the entire plan:
Do not allow one unfinished topic to destroy the next three weeks.
If Wednesday’s material was not completed:
Do not spend Thursday, Friday, Saturday, and Sunday endlessly trying to finish Wednesday.
Instead:
- Complete the highest-yield portion.
- Mark the unfinished material.
- Move forward with the schedule.
- Use the weekly catch-up block to return to it.
- Revisit it later during cumulative review.
A study plan only works if it keeps moving.
Phase 1 — FOUNDATION
Week 1 — Biomedical Sciences
Main Goal
Build the biological framework that supports pharmacology and clinical reasoning.
Study:
- anatomy and physiology
- biochemistry
- medical microbiology
- immunology
- genetics
- pathophysiology
High-Value Concepts
Biochemistry
- proteins and amino acids
- enzymes
- enzyme kinetics
- carbohydrates and lipids
- major metabolic pathways
- vitamins and coenzymes
Physiology
- cardiovascular
- respiratory
- renal
- endocrine
- CNS
- fluid and electrolytes
Microbiology
- bacterial structure
- Gram-positive vs Gram-negative organisms
- bacterial growth
- resistance
- viruses
- fungi
- parasites
- sterilization and disinfection concepts
Immunology
- innate vs adaptive immunity
- B cells and T cells
- antibodies
- MHC
- complement
- hypersensitivity
- vaccines
Genetics
- replication
- transcription
- translation
- mutations
- polymorphisms
- inheritance
Do Not Study These as Isolated Basic Sciences
Connect them to pharmacy.
For example:
- Enzymes → pharmacology + metabolism
- Microbiology → antimicrobial therapy
- Immunology → vaccines + biologics
- Genetics → pharmacogenomics
- Renal physiology → dosing + laboratory interpretation
End-of-Week Exam
Test biomedical sciences plus a few basic pharmacology and calculation questions.
Week 2 — Pharmacokinetics, Biopharmaceutics, and Calculations
This week establishes some of the most reusable concepts on the entire FPGEE.
Study:
- ADME
- bioavailability
- bioequivalence
- volume of distribution
- clearance
- half-life
- elimination-rate constant
- steady state
- loading and maintenance concepts
- first- vs zero-order kinetics
- compartment concepts
- therapeutic drug monitoring
Calculation Rotation
Practice:
- ratios and proportions
- concentration
- percentage strength
- molarity
- milliequivalents
- osmolarity
- infusion rates
- dose calculations
Learn Graphs, Not Only Formulas
Be comfortable interpreting:
- concentration-time curves
- AUC
- Cmax
- Tmax
- changes in clearance
- changes in volume of distribution
- changes in half-life
A formula is only useful if you understand what changes in the patient or drug will do to the result.
Week 3 — Medicinal Chemistry + Pharmaceutics
Medicinal Chemistry
Focus on concepts that help you reason rather than trying to memorize every structure.
Study:
- functional groups
- acids and bases
- pKa
- ionization
- lipophilicity and hydrophilicity
- stereochemistry
- drug metabolism
- structure-activity relationships
- pharmacophores
- important representative structures
Ask:
What chemical feature explains this drug’s behavior?
That question is often more useful than:
Can I redraw the whole molecule?
Pharmaceutics
Study:
- tablets
- capsules
- coatings
- excipients
- granulation
- powder flow
- solutions
- suspensions
- emulsions
- creams and ointments
- modified-release systems
- dissolution
- disintegration
- stability
- degradation kinetics
- shelf life
- manufacturing concepts
Connect dosage-form properties to:
- absorption
- bioavailability
- stability
- administration
- patient use
Week 4 — Pharmacology, Toxicology, Interactions, and Pharmacogenomics
Now bring the pharmaceutical sciences together.
Pharmacodynamics
Study:
- receptors
- agonists
- antagonists
- partial agonists
- inverse agonists
- potency
- efficacy
- dose-response curves
- receptor regulation
- signaling pathways
Drug Interactions
Understand mechanisms behind:
- CYP inhibition
- CYP induction
- transporters
- drug-drug interactions
- drug-food interactions
- drug-disease interactions
- drug-laboratory interactions
Toxicology
Study:
- common toxic exposures
- overdose patterns
- antidotes
- toxic effects
- supportive management concepts
Pharmacogenomics
Know important gene-drug relationships and—more importantly—what the result changes clinically.
High-value examples can include:
- HLA-related hypersensitivity risks
- thiopurine metabolism
- fluoropyrimidine metabolism
- irinotecan metabolism
- selected statin-related genetic considerations
- isoniazid acetylation
Do not memorize a gene merely as a flashcard.
Ask:
What medication decision changes because of this result?
Phase 2 — BUILD Clinical Reasoning
From Week 5 onward, every disease-state review should use a consistent framework.
For each condition know:
- Basic pathophysiology
- Treatment goals
- Major drug classes
- Mechanisms
- Important adverse effects
- Contraindications
- Drug interactions
- Monitoring
- Patient counseling
- How comorbidities alter the choice
Week 5 — Cardiovascular + Renal
Study:
- hypertension
- heart failure
- acute coronary syndromes
- dyslipidemia
- anticoagulation
- arrhythmias
- stroke concepts
- renal function
- important electrolytes
- common laboratory interpretation
Case Habit
Whenever you see a cardiovascular patient, check:
- blood pressure
- heart rate
- potassium
- renal function
- interacting medications
- anticoagulants or antiplatelets
- comorbid diabetes or kidney disease
Do not memorize cardiovascular drug lists without learning patient selection.
Week 6 — Endocrine + Diabetes
Study:
- diabetes
- insulin
- oral and injectable therapies
- hypoglycemia
- DKA/HHS concepts
- thyroid disorders
- adrenal disorders
- selected pituitary concepts
Focus on:
- mechanism
- adverse effects
- organ-function considerations
- monitoring
- patient-specific selection
Continue calculation practice during this week.
Week 7 — Infectious Diseases + HIV + Immunization
Study:
- antimicrobial classes
- mechanism of action
- resistance
- bug-drug relationships
- common infectious syndromes
- tuberculosis
- HIV
- antivirals
- opportunistic infection concepts
- vaccines
Do not memorize antibiotics only by spectrum.
Connect:
Organism → site of infection → patient factors → safest appropriate therapy
Week 8 — CNS, Psychiatry, Seizures, and Pain
Study:
- depression
- anxiety
- bipolar disorder
- schizophrenia
- seizure disorders
- Parkinson disease
- migraine
- pain management
- opioids
- substance-use concepts
- sleep-related topics
Focus heavily on:
- adverse effects
- monitoring
- interactions
- pregnancy considerations
- serotonin effects
- QT effects
- seizure threshold
- CNS depression
Week 9 — Oncology + Respiratory + GI + Musculoskeletal + Self-Care
This is a broad week.
Do not attempt to memorize every treatment regimen.
Focus on core patterns.
Oncology
Know:
- major chemotherapy classes
- characteristic toxicities
- supportive-care principles
- selected targeted therapies
- monoclonal antibodies
- important monitoring
Respiratory
Study:
- asthma
- COPD
- inhaler classes
- administration technique
- adverse effects
GI
Study:
- acid-related disorders
- nausea and vomiting
- constipation and diarrhea
- selected inflammatory GI conditions
Musculoskeletal
Study:
- gout
- osteoporosis
- rheumatoid arthritis
- selected multiple-sclerosis concepts
Self-Care
Do not ignore:
- OTC medications
- counseling
- contraindications
- natural products
Self-care is explicitly represented within the current clinical domain.
Phase 3 — INTEGRATE the Administrative and Evidence Domains
Many candidates postpone administrative sciences because they feel less familiar than pharmacology.
Do not make that mistake.
The current Social, Behavioral, and Administrative Sciences domain represents approximately 20% of scored questions.
That deserves dedicated preparation.
Week 10 — Biostatistics, Research Methods, and Evidence
Study:
- study designs
- randomized controlled trials
- cohort studies
- case-control studies
- bias
- confounding
- validity
- statistical tests
- p-values
- confidence intervals
- Type I and Type II errors
- power
- relative risk
- odds ratio
- ARR
- RRR
- NNT
- NNH
Do not learn statistics as formulas only.
You should be able to answer:
What does this number mean?
and:
Is this result statistically significant?
Drug Information and Evidence-Based Practice
Study:
- primary, secondary, and tertiary literature
- PubMed
- MeSH
- PICO
- guidelines
- drug-information resources
- literature evaluation
- information-source reliability
- MedWatch and safety-reporting concepts
Week 11 — U.S. Health Care Systems + Pharmacoeconomics + Management
International graduates may find this material unfamiliar because much of it relates specifically to U.S. pharmacy practice.
Study:
Health Care Systems
- Medicare
- Medicaid
- CMS
- insurance concepts
- health care delivery
- public health
- hospice
- health-system organization
Pharmacoeconomics
- cost-minimization
- cost-effectiveness
- cost-benefit
- cost-utility
- QALY
- incremental cost concepts
Management
- budgeting
- inventory
- procurement
- personnel management
- leadership
- risk management
- business planning
- financial concepts
Do not leave this material until the final days.
Week 12 — Ethics, Communication, Public Health, Regulation, and Behavior
Study:
- professional and regulatory principles represented in the current FPGEE outline
- relevant professional organizations
- biomedical ethics
- professional responsibility
- health literacy
- communication
- patient adherence
- cultural awareness
- behavior modification
- social determinants of health
- infection control
- quality improvement
- population health
Ask Scenario-Based Questions
Instead of asking:
What is autonomy?
ask:
Which action best respects patient autonomy in this situation?
Application is more durable than definition memorization.

Phase 4 — SIMULATE the Exam
You have now completed the major first-pass content.
Do not spend Weeks 13–16 simply rereading everything from page one.
These weeks should increasingly be driven by performance.
Week 13 — Pharmaceutical Sciences Repair Week
Return to the high-weight science domain.
Use your previous exams and error log to identify weaknesses in:
- calculations
- PK
- medicinal chemistry
- pharmacology
- pharmaceutics
- compounding
- pharmacogenomics
- toxicology
Daily Rule
Do not review everything equally.
Spend the most time on concepts you repeatedly miss.
Week 14 — Clinical Integration Week
Now work primarily through mixed patient cases.
Rotate:
- cardiovascular
- renal
- endocrine
- infectious disease
- CNS
- oncology
- respiratory
- GI
- musculoskeletal
- prevention and self-care
For every case ask:
- What is the active problem?
- What data matter?
- Is the current treatment indicated?
- Is it effective?
- Is it safe?
- Are there interactions?
- What should be monitored?
- What is the best next step?
This turns memorized pharmacology into clinical reasoning.
Week 15 — Mock Exam + Repair
This week is not:
Take mock → see score → move on.
Use:
MOCK → ANALYZE → REPAIR → RETEST
Take a comprehensive timed practice examination.
Then classify important misses:
- Knowledge
- Application
- Calculation
- Chemistry / Structure
- Data / Graph
- Misread
- Timing
Build the rest of the week around the largest recurring weaknesses.
Then retest those concepts using new questions.
Week 16 — Final High-Yield Review
The final week should become progressively lighter.
Do not attempt to relearn the entire FPGEE.
Focus on:
- previous mistakes
- formulas
- PK concepts
- calculations
- important medicinal chemistry patterns
- pharmacogenomics
- major interactions
- antidotes
- statistics
- important laboratory interpretation
- high-yield clinical monitoring
- management and health-system concepts you repeatedly forget
Final 3 Days
Three Days Before
Mixed high-yield review.
Use rapid-review sheets and your error log.
Two Days Before
Focus on:
- calculations
- PK
- statistics
- chemistry
- interactions
- pharmacogenomics
Keep the workload controlled.
Day Before
Very light review only.
Good choices:
- formulas
- genes
- structures you repeatedly miss
- important interactions
- rapid-review sheets
- previous errors
Avoid:
- a giant new chapter
- a full new textbook
- a marathon mock exam
- staying awake late trying to “finish everything”
At this point your job is to protect the knowledge you have built.
How Much Should You Study Each Day?
There is no universal number.
A working pharmacist with children and a full-time schedule cannot necessarily follow the same timetable as someone studying full-time.
Instead, build a plan you can repeat.
Working-Student Version
Monday–Thursday
2–3 focused hours
Include:
- main topic
- practice questions
- small calculations or chemistry block
Friday
- finish weekly content
- rapid review
- weekly exam
Weekend
Use one larger block for:
- correcting the weekly exam
- catching up on unfinished high-value material
- cumulative questions
- preparing the next week
Full-Time Study Version
A full-time student can expand each block rather than adding random new topics.
For example:
Morning
Main content
Early Afternoon
Questions and cases
Late Afternoon
Calculations / chemistry / PK
Evening
Error review + older material
The goal is still structured repetition, not simply more hours.
The 70/20/10 Rule for a Study Day
A useful RxBoardPrep planning model is:
70% — Current Priority
The main subject assigned for the day.
20% — Practice + Repair
Questions and review of mistakes.
10% — Maintenance
Older calculations, chemistry, statistics, formulas, or rapid review.
This is not an NABP requirement.
It is an RxBoardPrep planning tool designed to prevent older material from disappearing while you study new topics.
Do Not “Finish” Calculations
Calculations are not something you complete in Week 2 and never see again.
Keep rotating:
- ratios
- percentages
- concentrations
- molarity
- mEq
- osmolarity
- infusion
- dose calculations
- PK
- statistics
Short repeated practice is often more useful than one enormous calculation weekend.
Do Not “Finish” Medicinal Chemistry Either
Medicinal chemistry has the same problem.
If you study it intensively in Week 3 and never return to it, many structures and principles may fade by Week 12.
Keep a small rotation.
For example:
- Monday: Functional groups
- Tuesday: Metabolism
- Wednesday: Acid/base and ionization
- Thursday: SAR or pharmacophores
- Friday: Important structures
Ten or fifteen minutes can be enough for maintenance.
Use Questions to Decide What to Study Next
Your schedule should become more personalized over time.
In Week 1, the plan decides what you study.
By Week 13, your performance should decide much more of it.
Suppose your cumulative exams show:
- calculations strong
- pharmacology strong
- medicinal chemistry weak
- management weak
- biostatistics inconsistent
Then Week 13 should not give equal time to all five.
The weakness pattern should control the repair.
Your FPGEE Error Log
Keep a simple table:
| Question | Topic | Error Type | Why I Missed It | Repair |
|---|---|---|---|---|
| 12 | PK | Application | Confused Vd effect | Review concept + 3 cases |
| 24 | Biostatistics | Interpretation | CI meaning unclear | Relearn significance rule |
| 35 | Chemistry | Structure | Missed functional group | Structure review |
| 48 | Management | Knowledge | Inventory term unknown | Add to rapid-review sheet |
The purpose of the log is not documentation.
It is decision-making.
What If You Fall Behind?
Do not restart the entire 16-week plan.
Use this priority system:
Priority A — Must Finish
Major concepts that support many other topics.
Examples:
- pharmacology fundamentals
- PK
- calculations
- major clinical disease states
- biostatistics
- management fundamentals
Priority B — Complete Soon
Important but narrower topics.
Priority C — Return During Cumulative Review
Smaller details and lower-priority gaps.
The worst catch-up strategy is trying to perfectly finish everything before moving forward.
The Weekly Exam Rule
Every week should end with some assessment.
Early weeks:
mostly current material + a small cumulative component
Later weeks:
increasingly mixed and cumulative
By the final month, the student should not know which chapter a question comes from before reading it.
That is the point.
How to Know Whether the Plan Is Working
Do not measure progress only by:
“I finished 10 chapters.”
Look for:
- fewer repeated mistakes
- faster recognition of concepts
- better calculation setup
- stronger interpretation of graphs
- better medicinal chemistry recognition
- improved clinical elimination
- stronger administrative-science vocabulary
- increasing cumulative performance
- less forgetting of older material
- improved pacing
Those are signs that knowledge is becoming usable.
Use the Official Blueprint as Your Coverage Checklist
Your 16-week schedule should ultimately cover all four domains.
The current official outline includes:
Domain 1 — Foundational Biomedical Sciences
Topics such as:
- anatomy and physiology
- biochemistry
- microbiology
- immunology
- pathophysiology
Domain 2 — Pharmaceutical Sciences
Topics such as:
- calculations
- medicinal chemistry
- pharmacology and toxicology
- pharmaceutics and biopharmaceutics
- pharmacokinetics
- pharmacogenomics
- compounding
Domain 3 — Social, Behavioral, and Administrative Sciences
Topics such as:
- professional and regulatory principles
- health care systems
- pharmacoeconomics
- population health
- management
- communication
- biostatistics and research methods
- social and behavioral pharmacy
Domain 4 — Pharmacy Practice and Clinical Sciences
Topics such as:
- clinical pathophysiology
- patient information and assessment
- treatment decisions
- safety
- disease prevention
- personalized medicine
- evidence-based practice
- self-care
Do a formal coverage check around Week 12.
Anything completely untouched should be scheduled before the final mock phase.
Test the Plan With Practice
Reading a 16-week schedule is not the same as knowing whether your preparation is working.
Use mixed practice periodically to identify whether your biggest weakness is:
- pharmaceutical science
- calculations
- clinical reasoning
- biostatistics
- management
- biomedical science
Ready to test your FPGEE preparation?
Use the Free FPGEE Practice Exam — Set A as a checkpoint during your 16-week plan. Review what you miss and use the results to decide what needs extra time next.
Ready for another set? Try FPGEE Practice Exam — Set B.
You can also browse all Free Practice Exams.
After completing a practice exam:
- identify the topic
- classify why you missed it
- repair the weakness
- solve new questions
- return to cumulative practice
Use the result to decide what receives extra time in your next study block.
Need a More Structured FPGEE Study System?
Explore RxBoardPrep FPGEE Prep for organized content review, calculations, practice exams, clinical reasoning, and guided preparation.
Final Takeaway
The FPGEE is too broad to prepare for effectively with random daily reading.
A better 16-week approach is:
Weeks 1–4 — FOUNDATION
Build biomedical and pharmaceutical fundamentals.
Weeks 5–9 — BUILD
Apply those principles across major clinical disease states.
Weeks 10–12 — INTEGRATE
Master statistics, evidence, U.S. health care systems, management, ethics, communication, and public health.
Weeks 13–16 — SIMULATE
Repair weak areas, complete mixed cases, take mock exams, and progressively narrow the final review.
Throughout all 16 weeks:
STUDY → PRACTICE → TEST → REPAIR → REVISIT
Do not wait until the final month to discover what you cannot apply.
And do not measure preparation by how many pages you have read.
Measure it by how reliably you can solve a question when nobody tells you which chapter it came from.
Frequently Asked Questions
Is 16 weeks enough to prepare for the FPGEE?
For many candidates, 16 weeks can provide a useful structured preparation window if study is consistent and prior pharmacy knowledge is reasonably intact. Candidates returning after a long period away from pharmacy or studying very limited hours may need longer.
How many hours per day should I study for the FPGEE?
There is no universal requirement. A repeatable 2–3 focused hours on working days can be more useful than an unrealistic schedule that collapses after one week. Full-time candidates can expand the study and practice blocks.
Should I study calculations every day?
Regular calculation practice is useful because calculation fluency can decline when the topic is left untouched for weeks. Short repeated practice can be incorporated throughout the 16-week plan.
Which FPGEE domain should receive the most study time?
The current official blueprint gives Pharmacy Practice and Clinical Sciences the largest approximate weight at 37%, followed by Pharmaceutical Sciences at approximately 31%. However, individual weaknesses should also influence study time.
When should I begin practice questions?
Week 1. Questions should be part of learning, not something saved until after all reading is complete.
When should I start taking cumulative exams?
Begin with small cumulative components early. By the second half of the plan, weekly exams should increasingly mix old and new material.
What should I do if I fall behind?
Do not restart the whole schedule. Complete the highest-value unfinished concepts, mark the remainder for catch-up, and keep moving. Use later cumulative-review weeks to repair remaining gaps.
Should I memorize every medicinal chemistry structure?
No. Learn high-value representative structures and the chemical principles that explain drug behavior, including functional groups, ionization, metabolism, stereochemistry, pharmacophores, and important SAR patterns.
Is pharmacy management really important for the FPGEE?
Yes. Social, Behavioral, and Administrative Sciences accounts for approximately 20% of scored questions, and the current outline includes management, health care systems, pharmacoeconomics, communication, public health, professional/regulatory concepts, and biostatistics/research methods.
What should I study during the final week?
Prioritize previous mistakes, formulas, calculations, PK, statistics, important chemistry patterns, interactions, pharmacogenomics, clinical monitoring, management, health-system concepts, and rapid-review material. Avoid trying to learn large new subjects immediately before the exam.
More FPGEE Resources
Start with the 2026 FPGEE Content Outline Explained to confirm what the blueprint covers.
Test your progress with the Free FPGEE Practice Exam — Set A, then move on to FPGEE Practice Exam — Set B.
Continue with the rest of the RxBoardPrep NAPLEX and FPGEE study guides.
If you are comparing preparation options, you can also review course pricing.
Sources and Methodology
Official source: National Association of Boards of Pharmacy. Foreign Pharmacy Graduate Equivalency Examination (FPGEE) Content Outline. Official PDF
The current outline organizes the examination into four domains with approximate weights of:
- Foundational Biomedical Sciences — 12%
- Pharmaceutical Sciences — 31%
- Social, Behavioral, and Administrative Sciences — 20%
- Pharmacy Practice and Clinical Sciences — 37%
RxBoardPrep planning methodology: This 16-week framework applies a structured cycle of content study, daily question practice, repeated calculations and medicinal-chemistry maintenance, cumulative weekly assessment, error classification, targeted repair, and final mock-exam integration.
This schedule is an educational planning model and is not an official NABP study schedule. Individual candidates should adjust the timeline according to baseline knowledge, work obligations, available study time, and performance.
RxBoardPrep is an independent pharmacy education platform and is not affiliated with or endorsed by NABP. FPGEE is a registered trademark of the National Association of Boards of Pharmacy.
